Frontotemporal lobar degeneration
Key Images
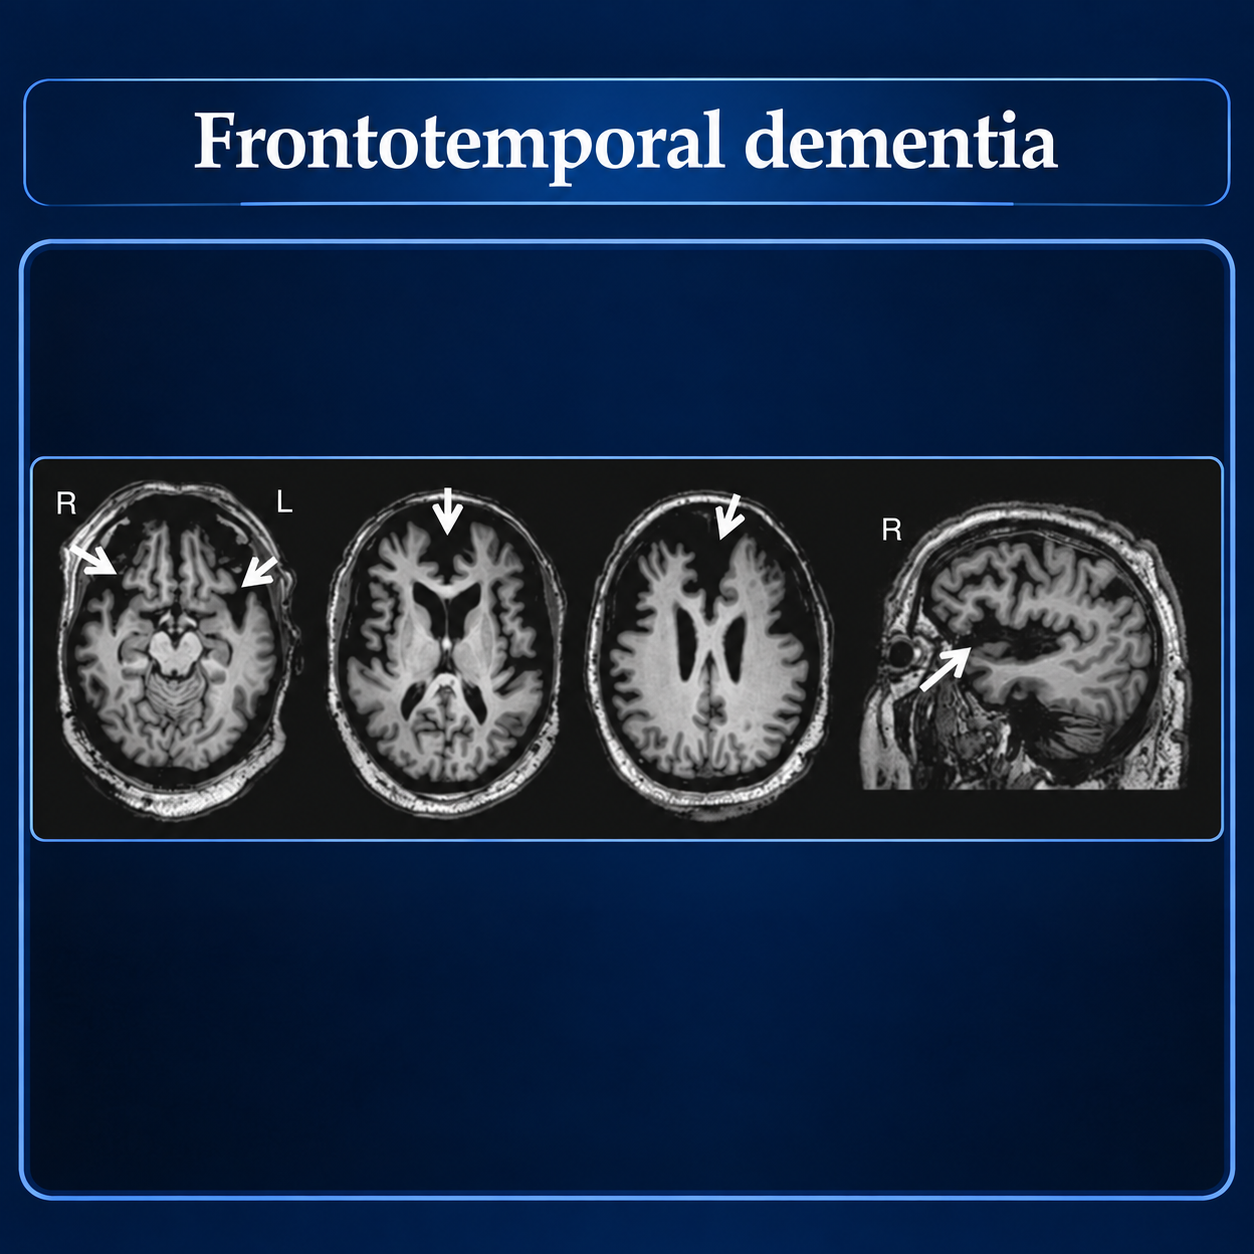
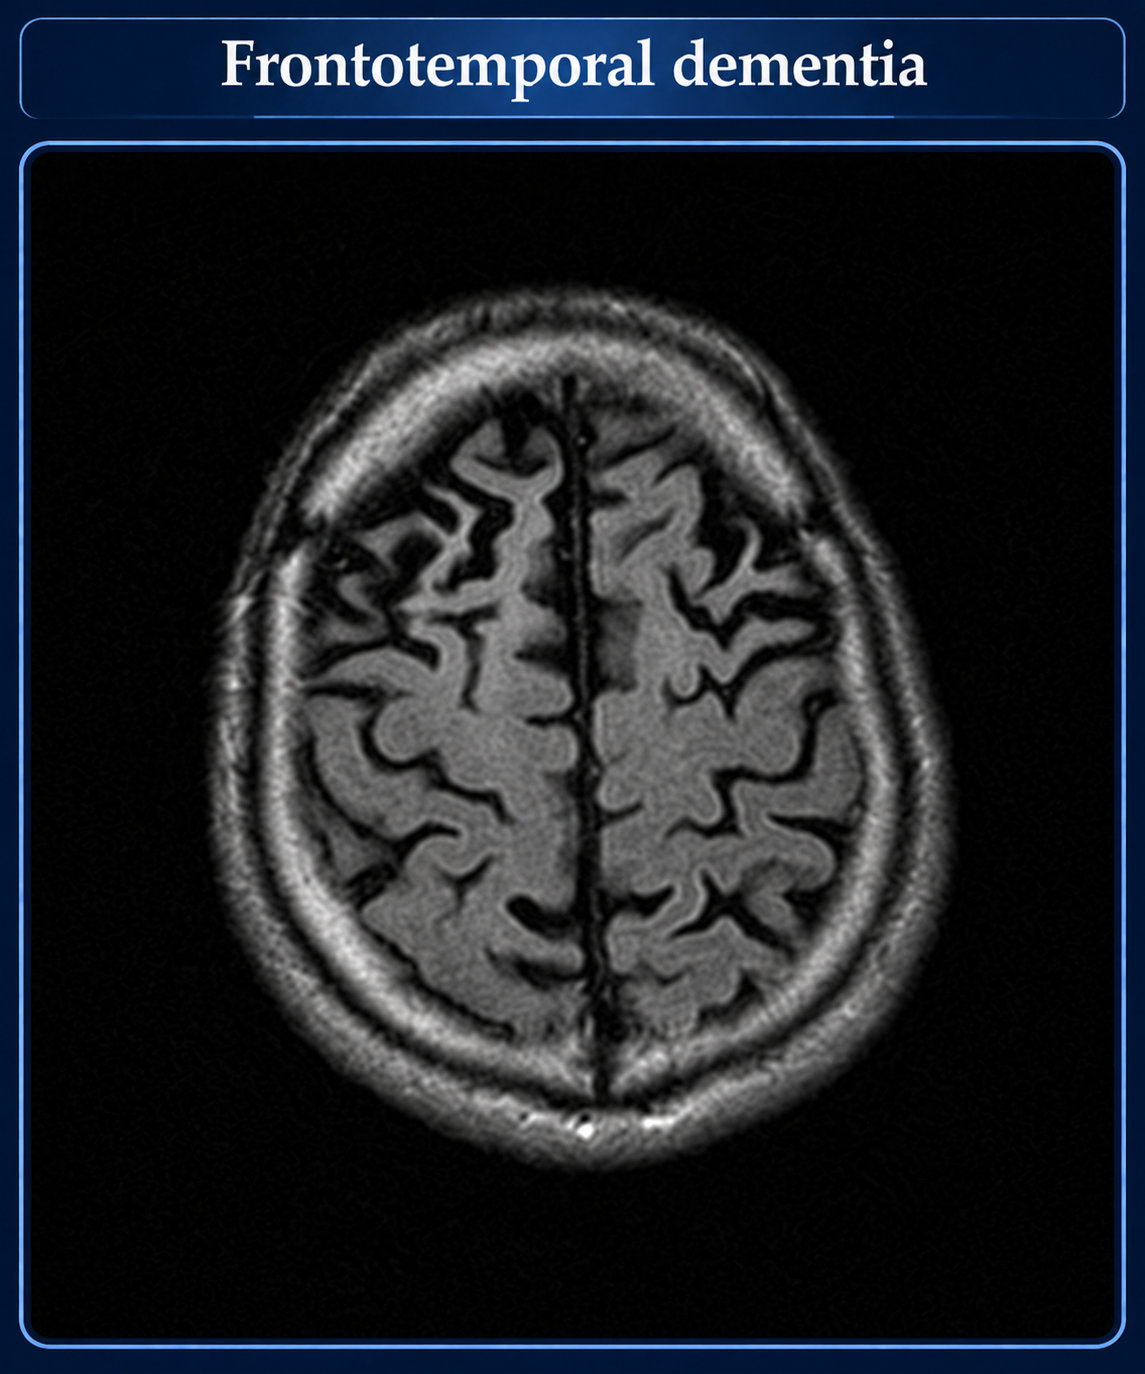
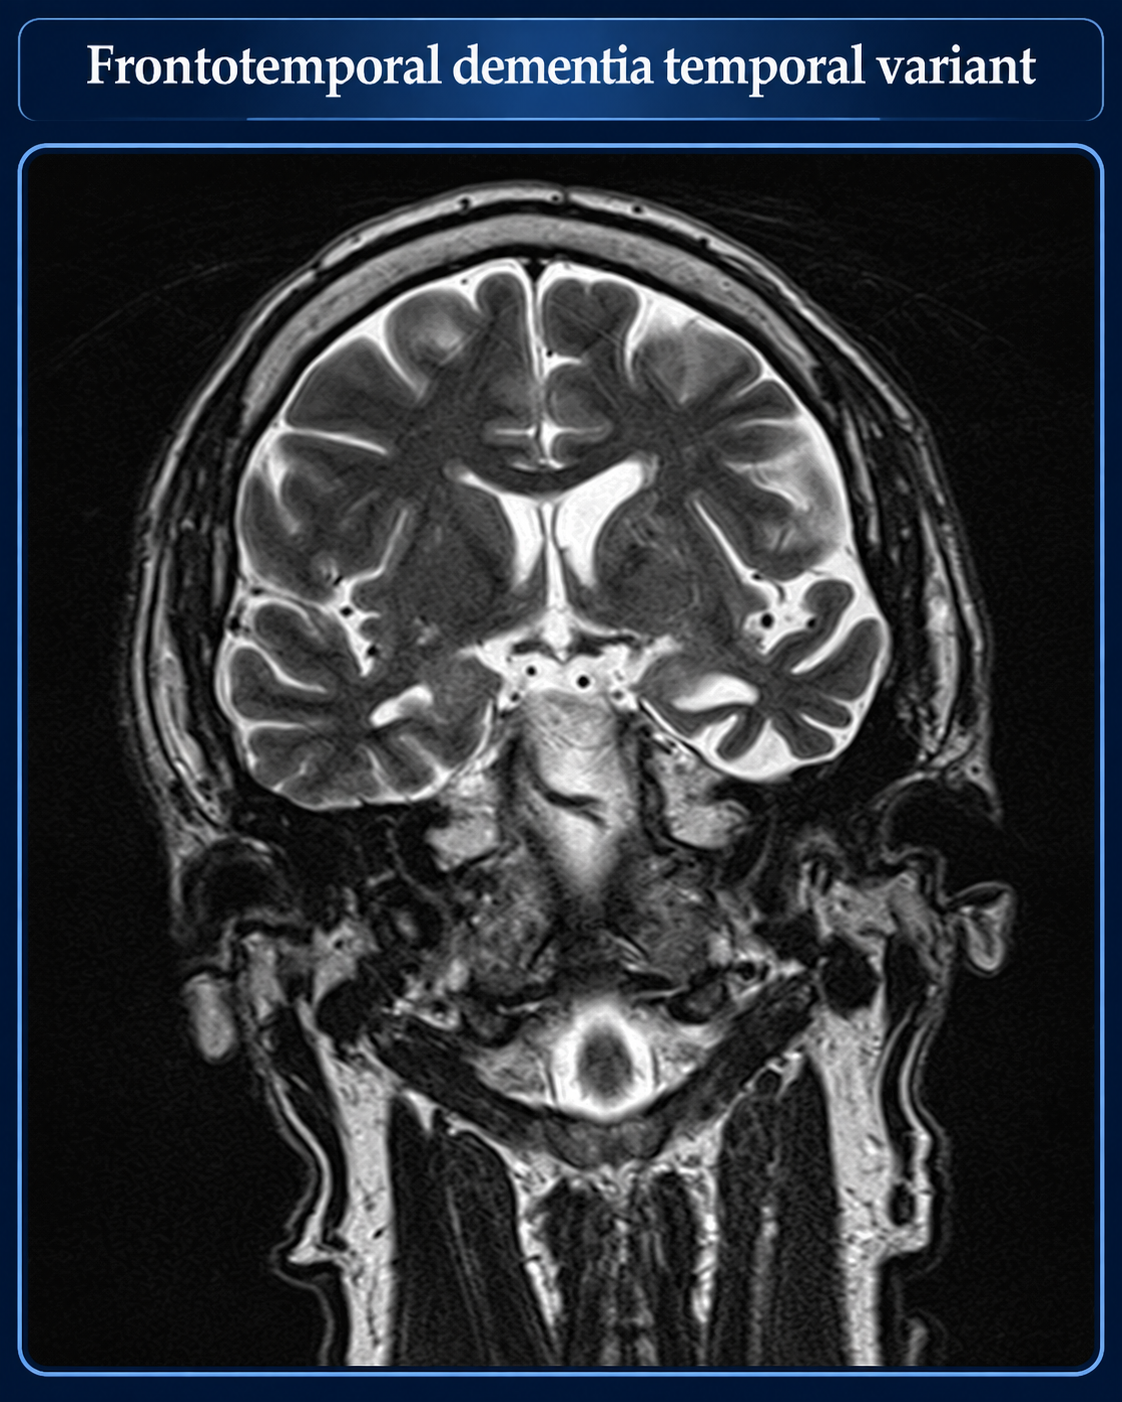
Look For First
- Focal atrophy of frontal and/or temporal lobes, often asymmetric depending on genotype and clinical phenotype
- Pattern of regional atrophy that correlates with specific FTD syndrome: bilateral frontal (bvFTD), left temporal (semantic PPA), left insula/Broca area (nonfluent PPA)
- Associated motor signs on imaging such as features of ALS, corticobasal degeneration, or progressive supranuclear palsy
Key Image Findings
- Bilateral frontal lobe atrophy is the dominant pattern in behavioral variant FTD (bvFTD), the most common presentation.
- Semantic variant PPA shows left temporal lobe atrophy with relative sparing of the insula and superior temporal gyrus.
- Nonfluent/agrammatic variant PPA demonstrates left insula and frontal operculum atrophy, including involvement of Broca's area.
- FTLD-FUS pathology is uniquely characterized by bilateral caudate nuclei atrophy, distinguishing it from other FTLD subtypes.
- FTLD-TDP associated with GRN mutation typically shows right frontal, lateral temporal, and parietal lobe atrophy, often with marked asymmetry between hemispheres.
- FTLD-TDP associated with C9orf72 mutation demonstrates bilateral hemispheric atrophy with a more generalized pattern of involvement.
- FTLD-tau associated with MAPT mutation characteristically shows bilateral temporal lobe atrophy.
- Regional atrophy patterns may overlap with imaging features of amyotrophic lateral sclerosis, corticobasal degeneration, or progressive supranuclear palsy depending on the motor variant involved.
Differential Diagnosis
- Alzheimer disease: typically shows medial temporal lobe and hippocampal atrophy with relative sparing of frontal lobes early in disease, whereas FTLD shows predominant frontal/temporal cortical atrophy.
- Lewy body dementia: usually presents with more generalized cortical atrophy and may show selective posterior parietal involvement, unlike the focal frontal/temporal pattern of FTLD.
- Vascular dementia: characterized by vascular lesions, white matter changes, and watershed infarcts, whereas FTLD shows focal cortical atrophy without primary vascular pathology.
- Primary psychiatric disorders: neuroimaging is typically normal in pure psychiatric disease, whereas FTLD demonstrates objective focal atrophy patterns on structural MRI.
- Logopenic variant PPA: often underpinned by Alzheimer pathology rather than FTLD pathology, typically showing temporoparietal atrophy rather than frontal/insular involvement.
Discussion
FTLD encompasses a pathologically heterogeneous group defined by misfolded proteins (TDP-43, tau, or FUS), and each pathological subtype correlates with specific regional atrophy patterns that aid in diagnosis.
Pick bodies are intracytoplasmic spherical inclusions found in Pick disease (old terminology). They are composed of tau fibrils (thus Pick disease is a tauopathy) arranged in a disorderly array. Although tau protein is a major component a number of other protein products are present, including ubiquitin and tubulin
The three major genetic causes (C9orf72, GRN, and MAPT) show distinct asymmetry and laterality patterns: GRN tends to be markedly asymmetric with right hemisphere predominance, C9orf72 is bilateral and generalized, and MAPT shows bilateral temporal involvement.
Clinical phenotype alone cannot reliably predict underlying pathology, making imaging a complementary diagnostic tool that can support genetic and pathological classification.
Approximately 20-30% of FTLD is familial with autosomal dominant inheritance, while 70-80% is sporadic, and imaging patterns may be helpful in stratifying genetic risk.
FTLD occurs at a younger age than Alzheimer disease (typically 40-60 years, with 10% diagnosed before age 45) and ranks second only to Alzheimer disease as a cause of dementia in patients under 65 years.
No disease-modifying therapy is currently approved; imaging biomarkers are under development as potential treatment-response measures in ongoing clinical trials.
Reporting Pearls
Describe the location and extent of focal atrophy (unilateral vs bilateral, symmetric vs asymmetric) and correlate the pattern with the clinical phenotype: "focal bilateral frontal atrophy compatible with behavioral variant FTD" or "left temporal lobe atrophy consistent with semantic variant primary progressive aphasia," noting any asymmetry that may suggest genetic subtypes such as GRN mutations (right-predominant) or C9orf72 (bilateral generalized) involvement.
Pitfalls
- Confusing FTLD atrophy patterns with normal aging-related brain changes; FTLD atrophy is focal and disproportionate in specific regions, not generalized age-appropriate involution.
- Failure to recognize that asymmetric right-predominant frontal and temporal atrophy suggests GRN-related FTLD, while bilateral generalized atrophy suggests C9orf72 mutations.
- Attributing language deficits to Alzheimer disease based on atrophy pattern alone; logopenic variant PPA is often Alzheimer pathology with temporoparietal atrophy, whereas nonfluent PPA shows insular/Broca area atrophy in FTLD-TDP.
- Missing the overlap features: motor neuron disease signs, parkinsonian changes, or other extrapyramidal features that may coexist with FTLD atrophy patterns, particularly in ALS-FTD spectrum disorders.