Basal Ganglia Mineralization
Key Images
Look For First
- Bilateral symmetric T2/T2* hypointensity in globus pallidus on MRI or hyperattenuation on CT
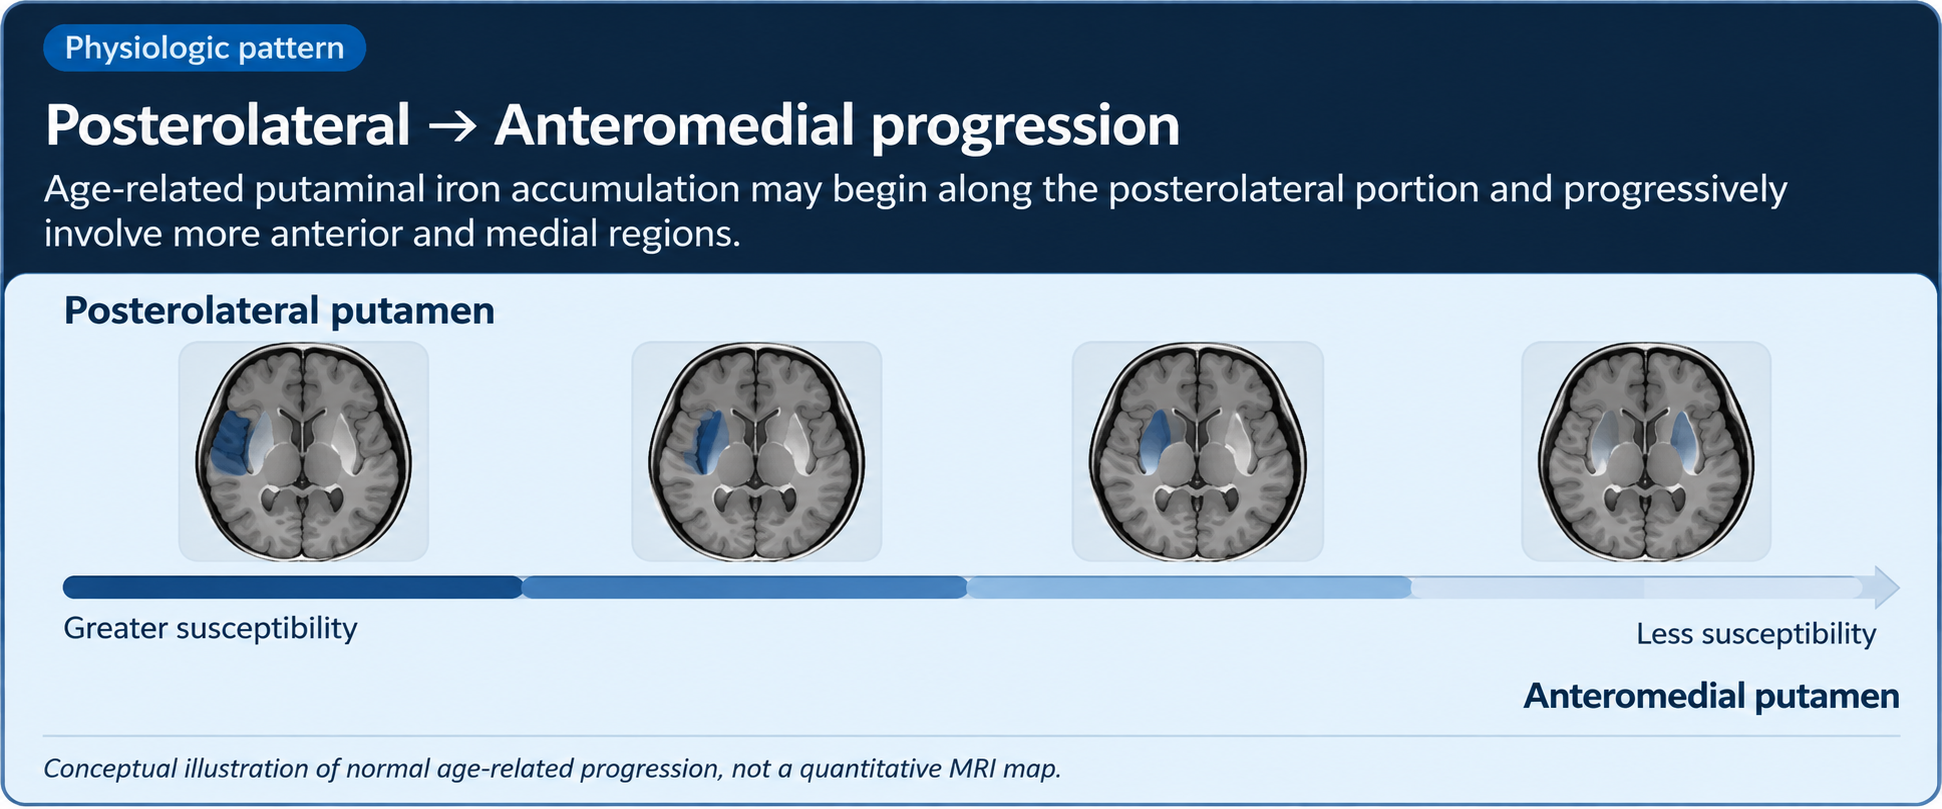
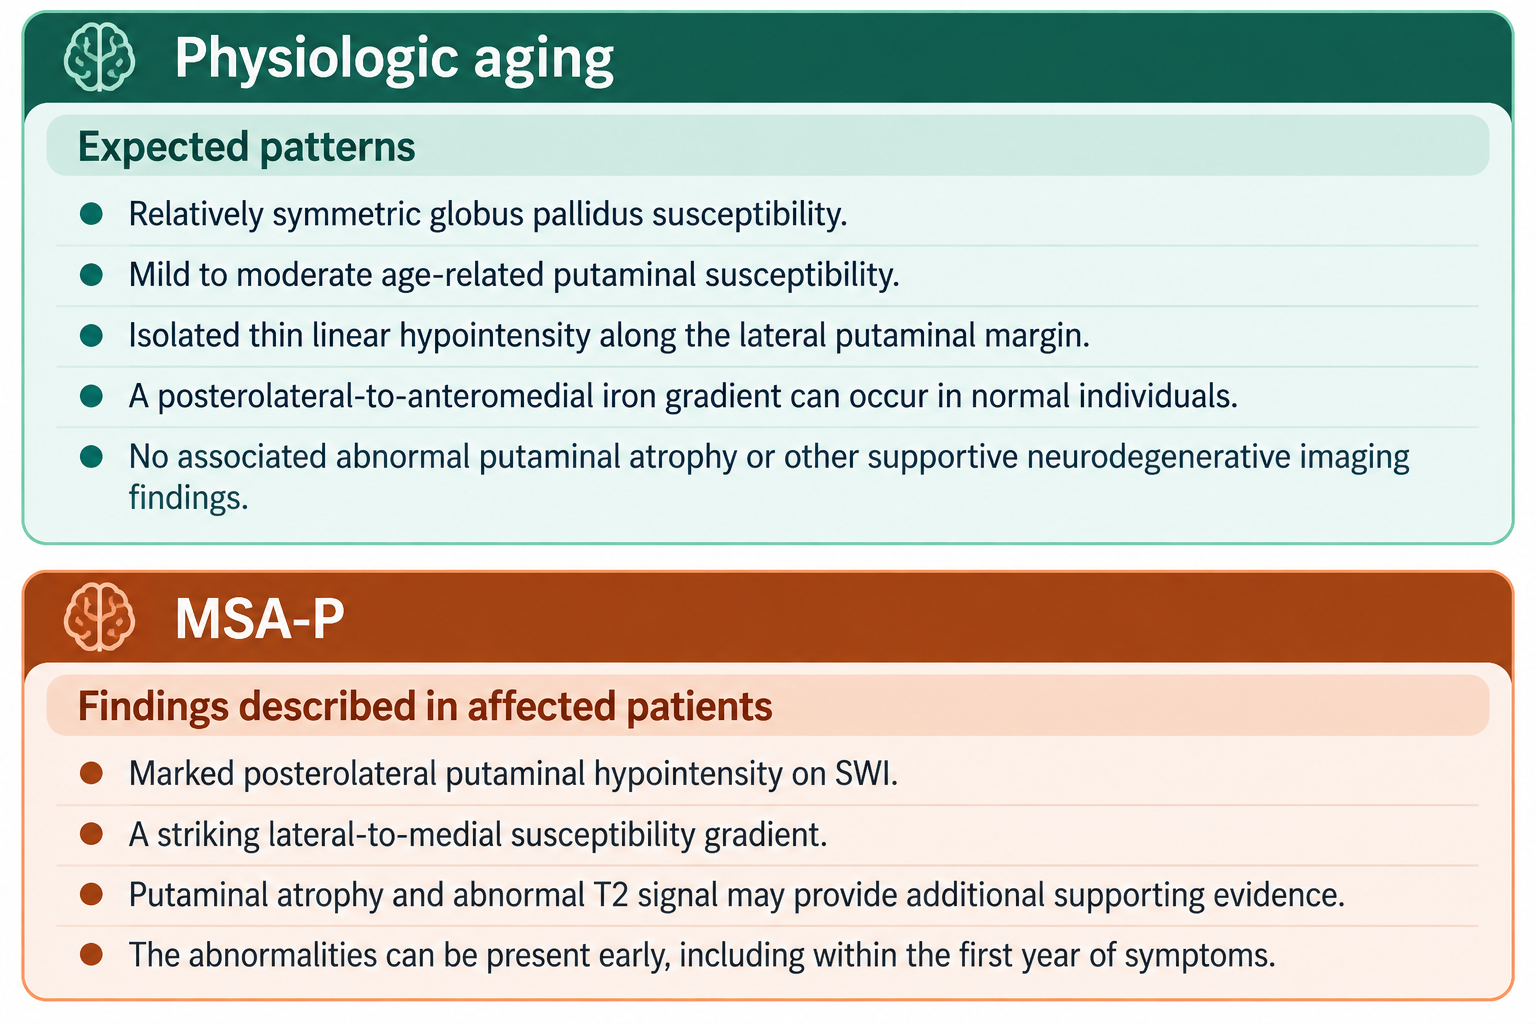
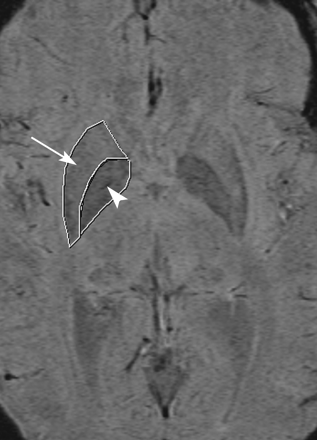
- Posterolateral-to-anteromedial iron gradient in putamen, which may be normal with aging
- Absence of parenchymal abnormalities, mass effect, or clinical neurologic symptoms
Key Image Findings
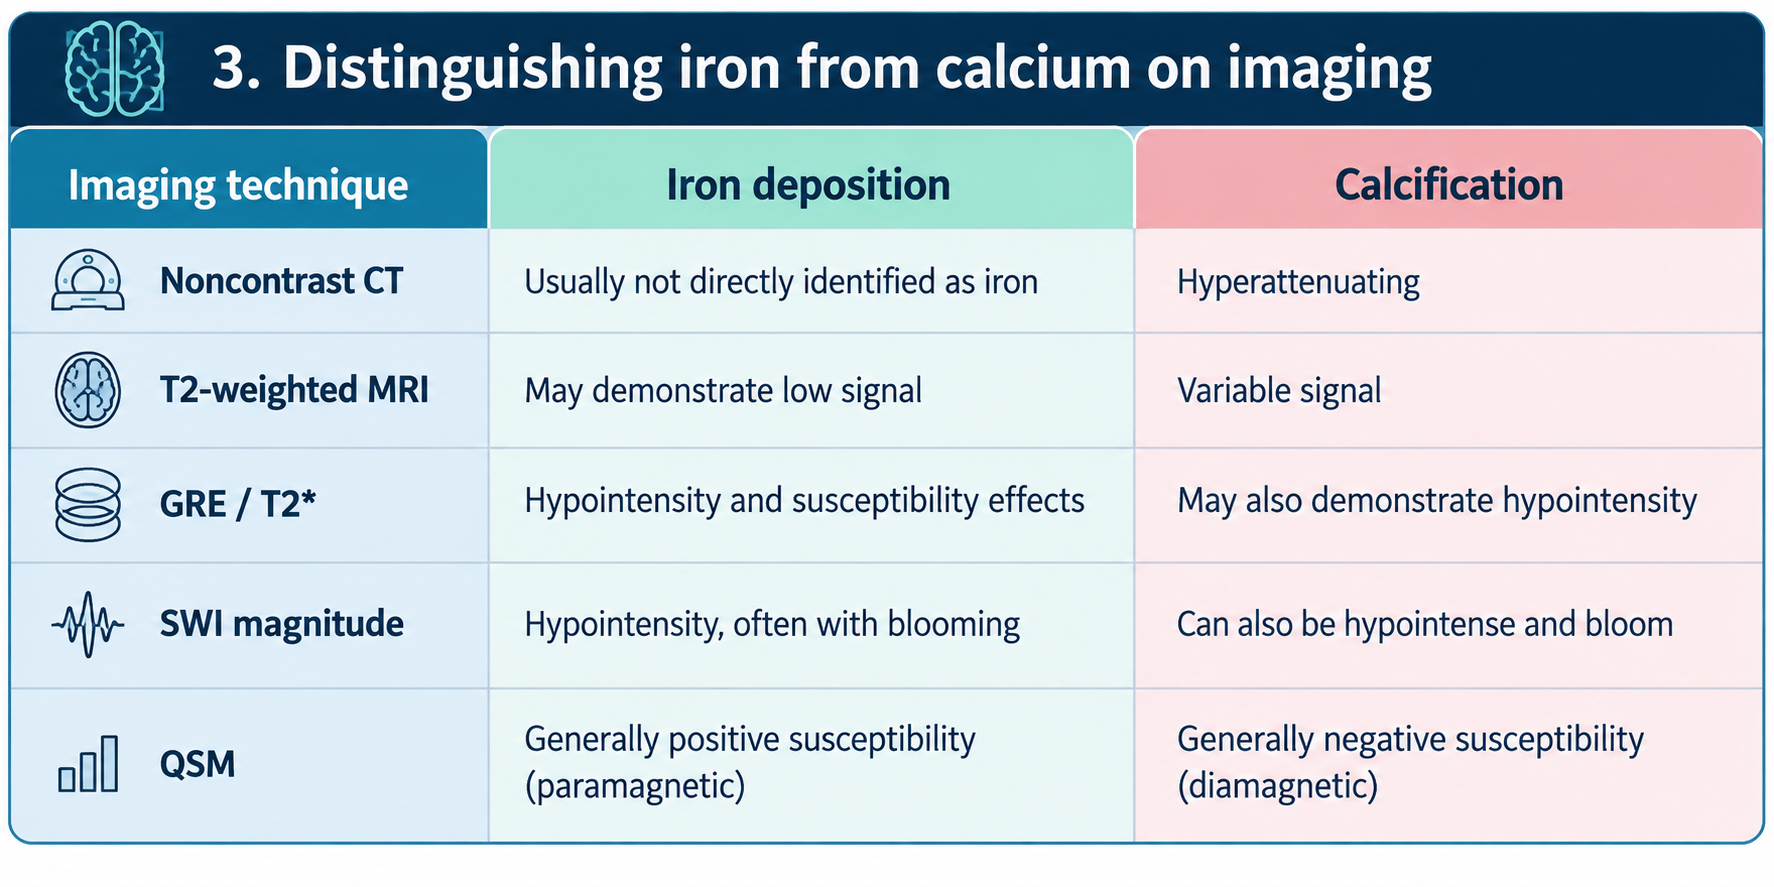
- Physiologic iron deposition produces susceptibility-related hypointensity on T2*, GRE, SWI, and QSM sequences; iron is paramagnetic with positive susceptibility on QSM.
- Calcium deposition appears hyperattenuating on noncontrast CT but is not directly visible as calcification on conventional MRI; calcium is diamagnetic with negative susceptibility on QSM.
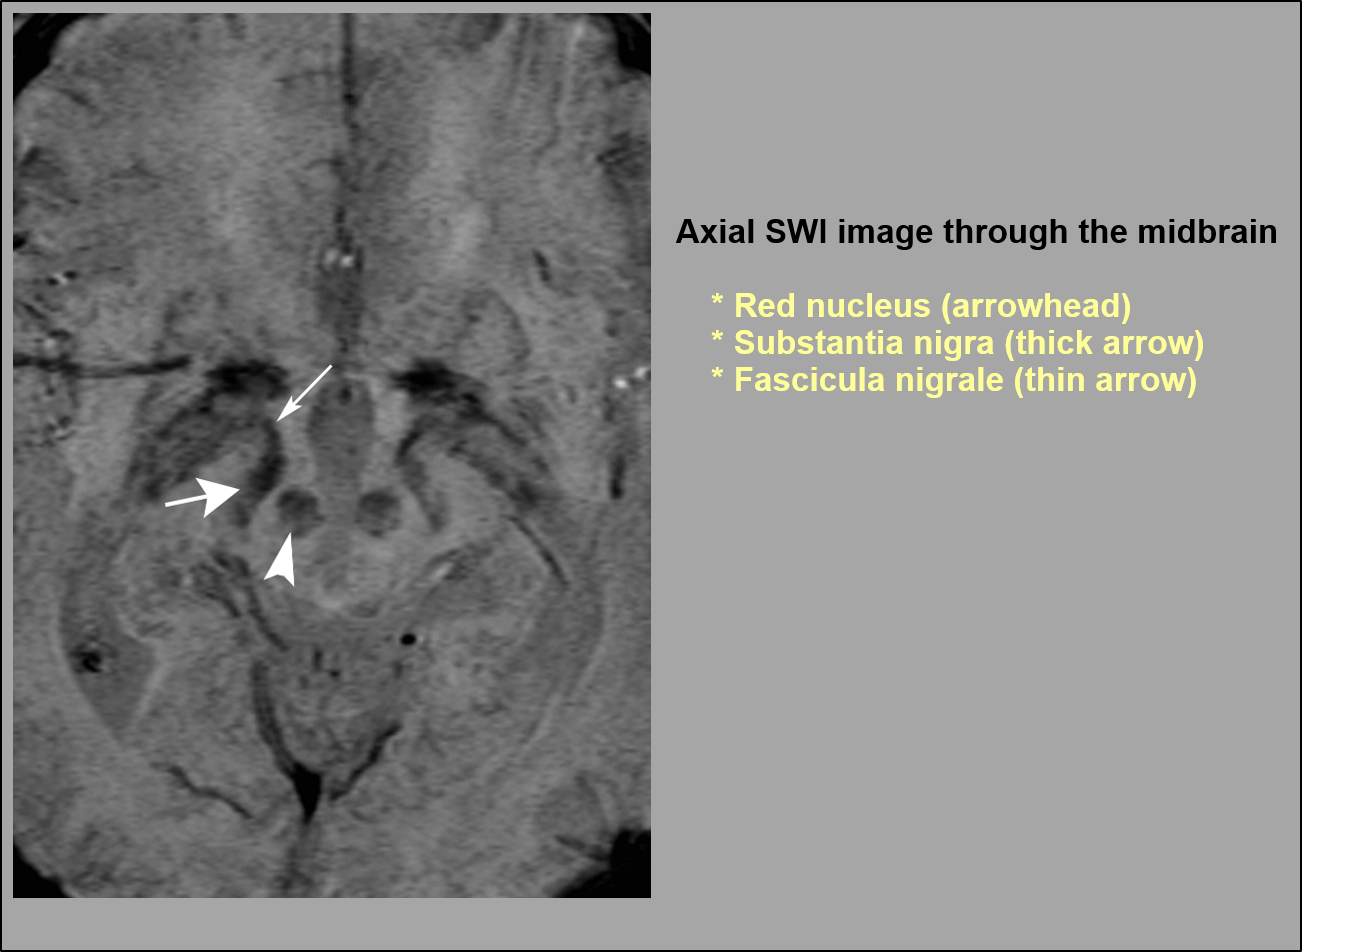
- Globus pallidus normally accumulates iron early (marked increase in childhood) with signal approaching plateau by fifth decade, while substantia nigra and red nucleus continue gradual decrease throughout life.
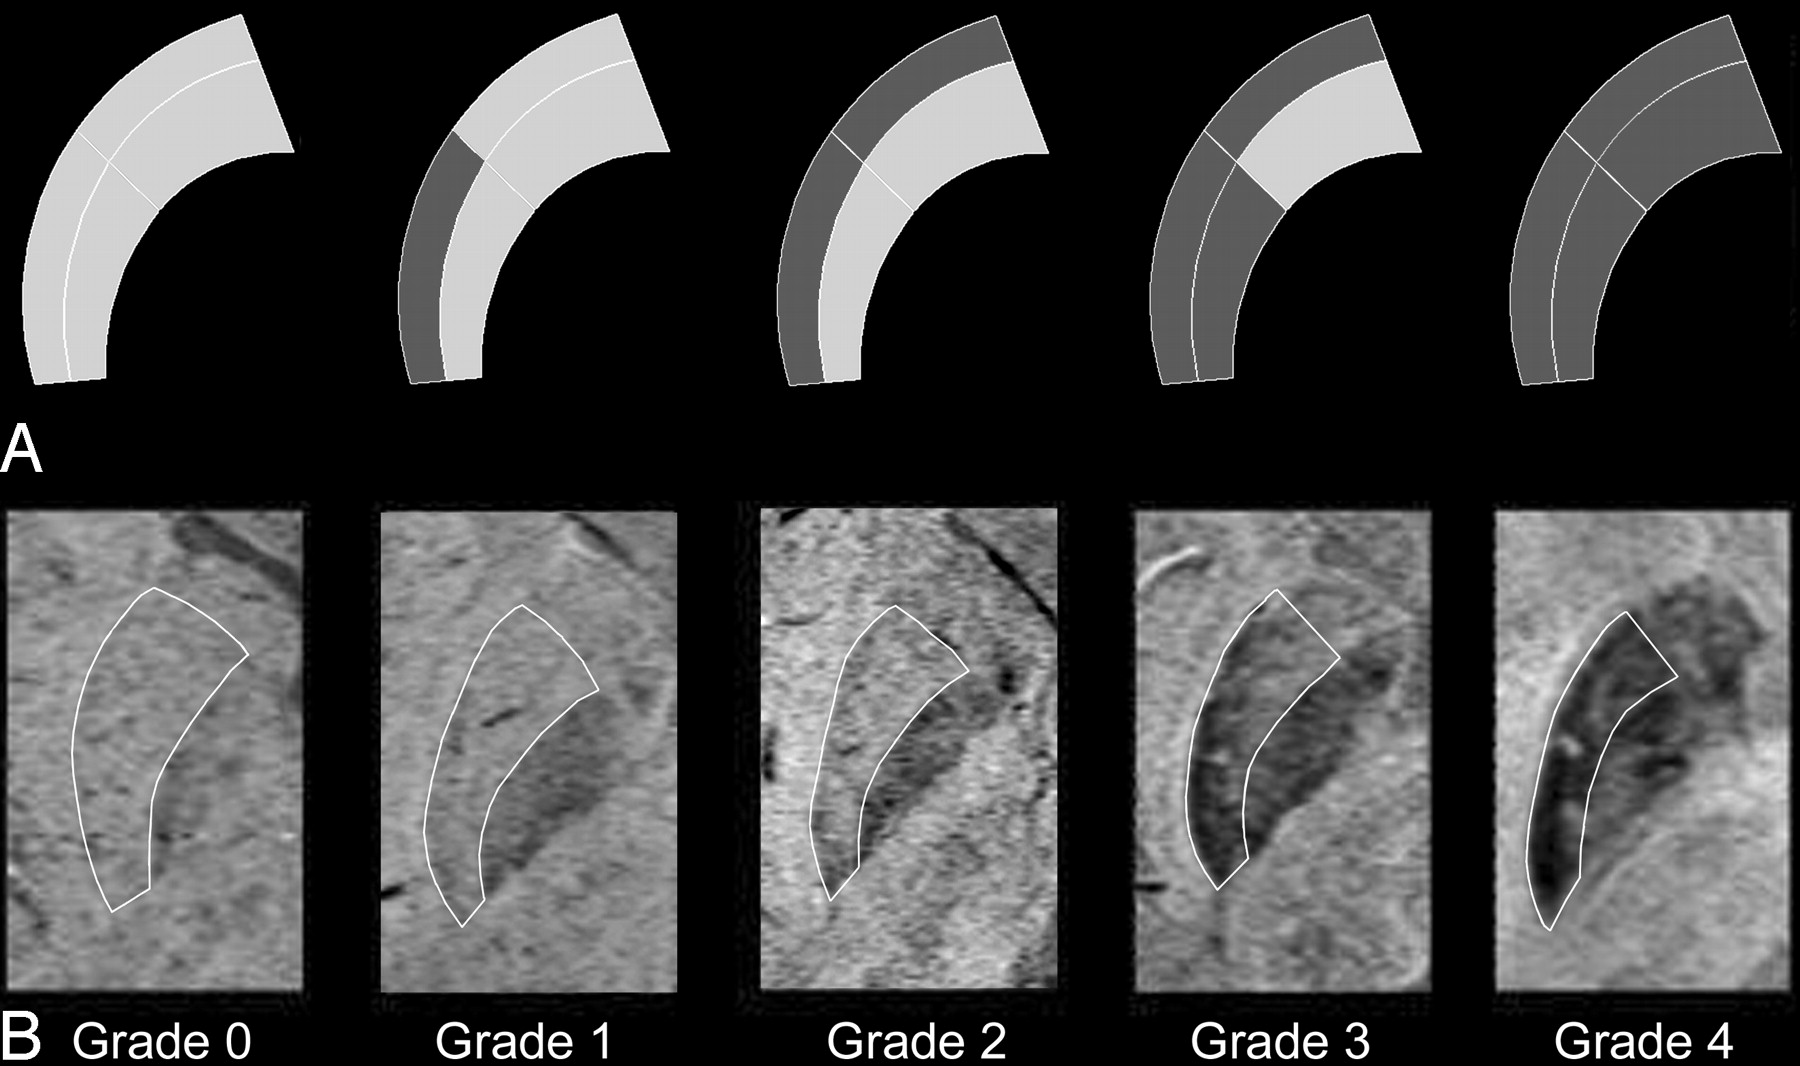
- Physiologic putaminal iron deposition typically begins posterolaterally and progresses anteromedially, creating a normal susceptibility gradient from lateral to medial; isolated thin linear lateral rim may be physiologic.
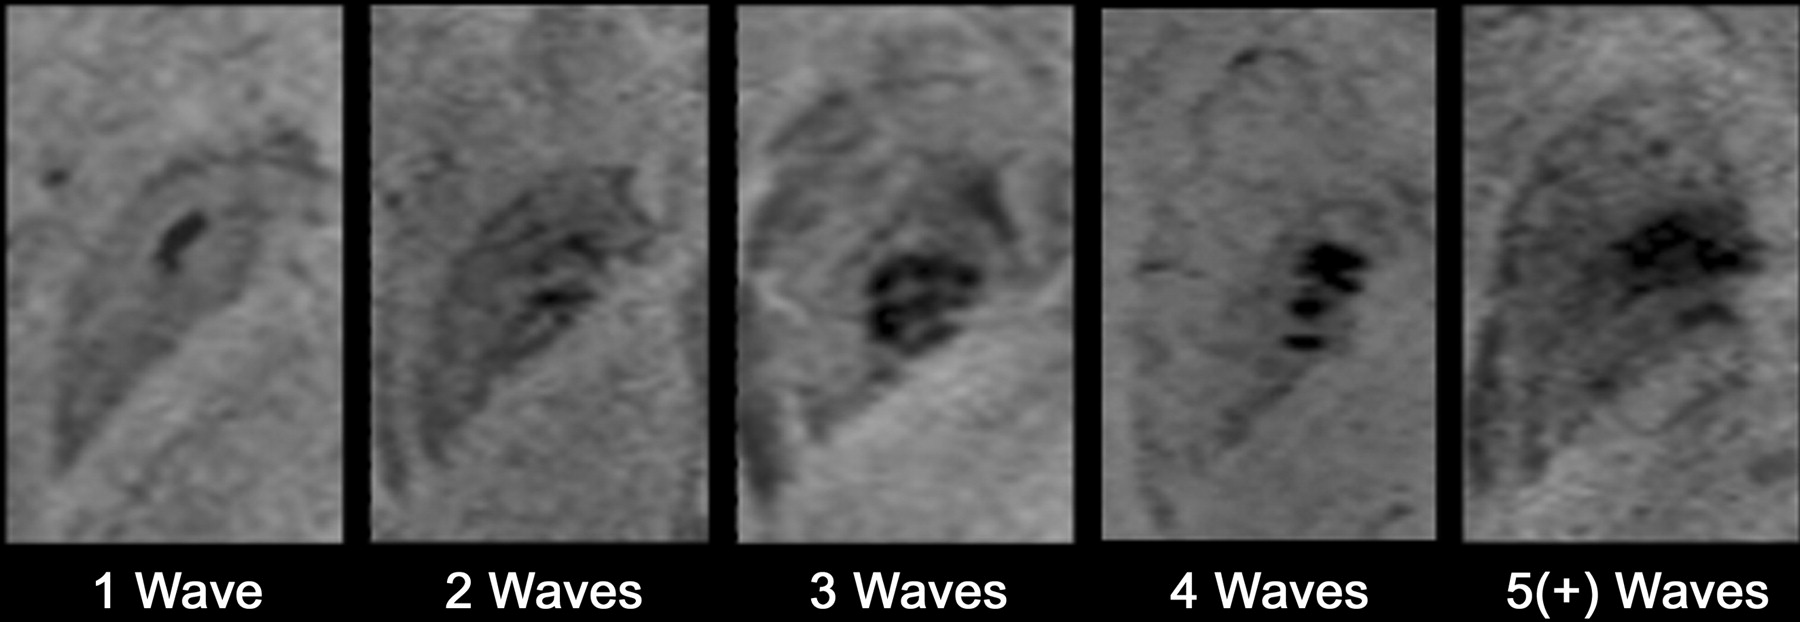
- On SWI, medial and lateral bands of mineralization in globus pallidus may create a wavelike appearance; multifocal T2* hypointensities may concentrate around lenticulostriate arteriole entry points in older individuals.
- Physiologic pallidal calcification occurs in 15-20% of elderly individuals without basal ganglia dysfunction symptoms; these deposits are typically small, punctate, and vascular (within tunica media and elastic laminae of small arteries).
- Distinguishing iron from calcium requires integration of CT (calcification is hyperattenuating) and MRI; QSM can reliably differentiate based on magnetic susceptibility (iron paramagnetic/positive; calcium diamagnetic/negative).
- Age-adjusted Total Calcification Score thresholds help identify disproportionate mineralization: 0 points below age 40, 4 points at ages 40-60, and 5 points above age 60.
Differential Diagnosis
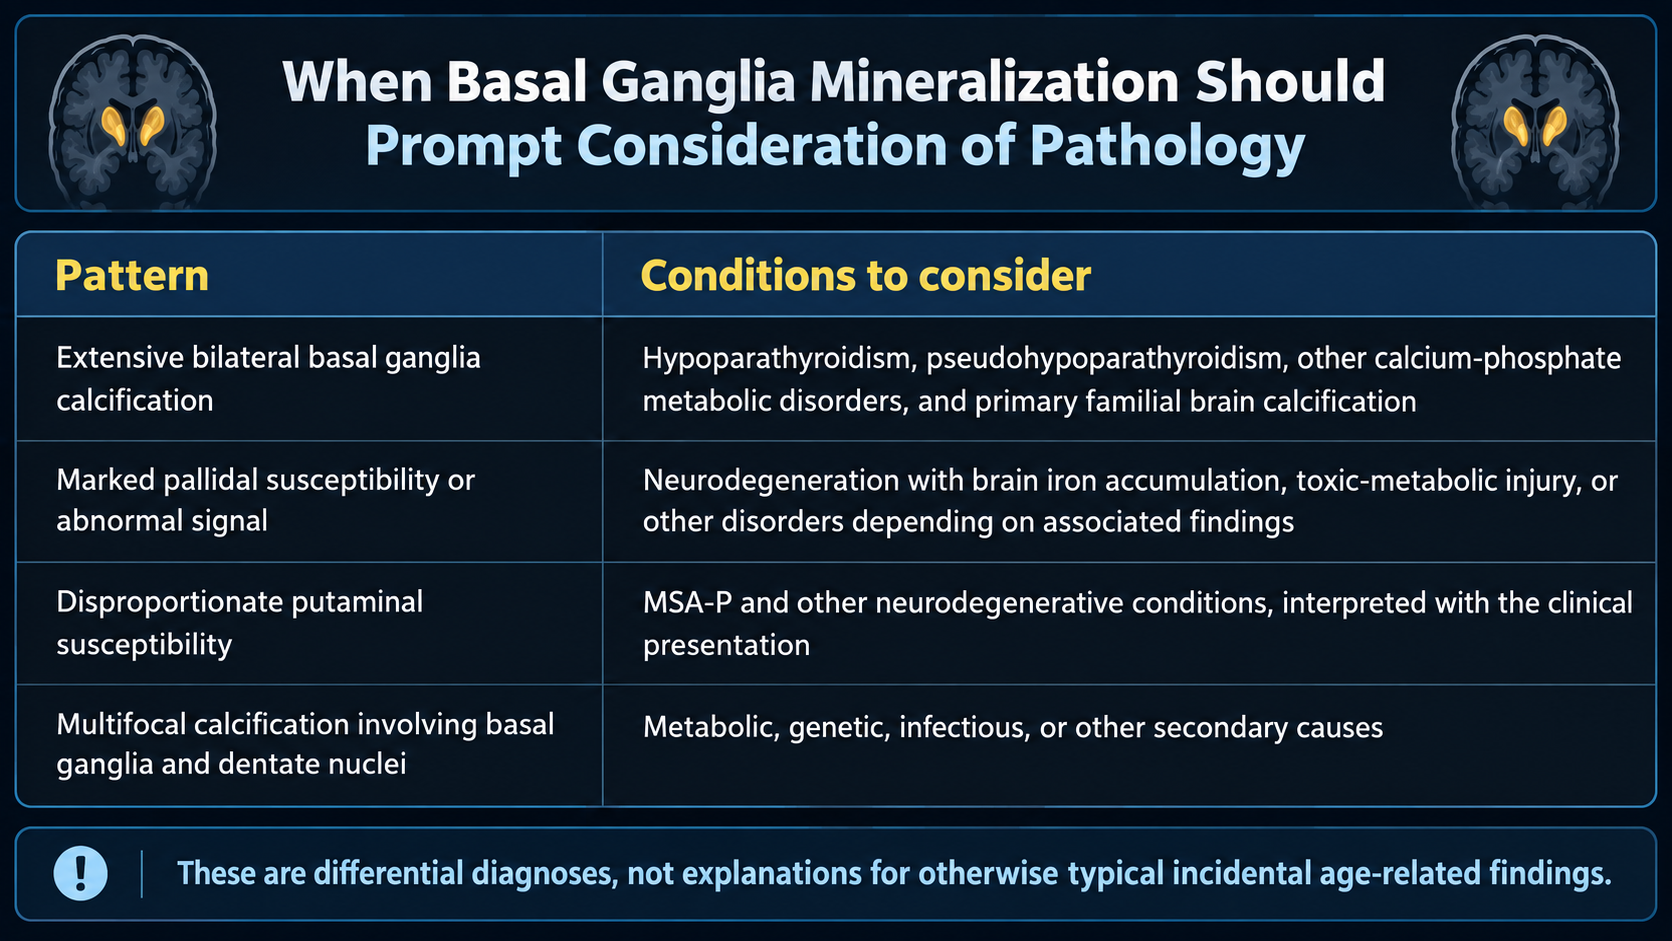
- MSA-parkinsonian type: Marked posterolateral putaminal hypointensity with striking lateral-to-medial susceptibility gradient, associated putaminal atrophy, and abnormal T2 signal; distinguished from physiologic by severity, distribution, and supportive neurodegenerative features.
- Primary familial brain calcification (PFBC): Extensive bilateral basal ganglia and possibly dentate nuclei calcification; occurs in younger patients or with positive family history; differentiated by involvement of multiple nuclei and young age of presentation.
- Hypoparathyroidism/pseudohypoparathyroidism: Extensive bilateral basal ganglia and dentate nuclei calcification with abnormal calcium-phosphate metabolism; differentiated by laboratory findings and involvement beyond globus pallidus.
- Chronic kidney disease or secondary metabolic calcification: Extensive calcification involving multiple structures (putamen, thalamus, dentate nuclei, cortex, white matter); differentiated by renal dysfunction, abnormal phosphate and PTH levels.
- Toxic-metabolic injury or neurodegeneration with brain iron accumulation: Marked pallidal or multifocal susceptibility changes with progressive clinical symptoms; differentiated by clinical presentation and toxin/metabolic exposure history.
- Infection or toxic exposure (congenital infections, heavy metal exposure): Calcification in atypical locations with clinical history of infection or exposure; differentiated by distribution pattern and clinical context.
Discussion
Iron is essential for normal brain metabolism, mitochondrial function, and myelination; physiologic accumulation in deep gray nuclei is regionally selective and age-dependent rather than uniformly distributed.
The exact mechanism of age-related iron deposition in basal ganglia remains incompletely understood but may involve vascular and cellular iron homeostasis changes over time.
Physiologic calcification in globus pallidus is primarily vascular in nature, occurring within vessel walls of small arteries; it is frequently incidental and benign without clinical correlation.
The posterolateral-to-anteromedial gradient of putaminal iron is an important normal variant reflecting differences in regional arterial supply; its presence alone does not indicate MSA-P without other supporting features.
When distinguishing physiologic from pathologic mineralization, clinical integration is essential: patient age, imaging symmetry and extent, parenchymal abnormalities, associated atrophy, and clinical symptoms must all be considered together.
Disproportionate basal ganglia calcification for age, involvement of non-typical sites (putamen, thalamus, dentate nuclei, cortex, white matter), marked asymmetry, or progressive neurologic symptoms warrant evaluation for metabolic, genetic, infectious, or toxic etiologies.
Reporting Pearls
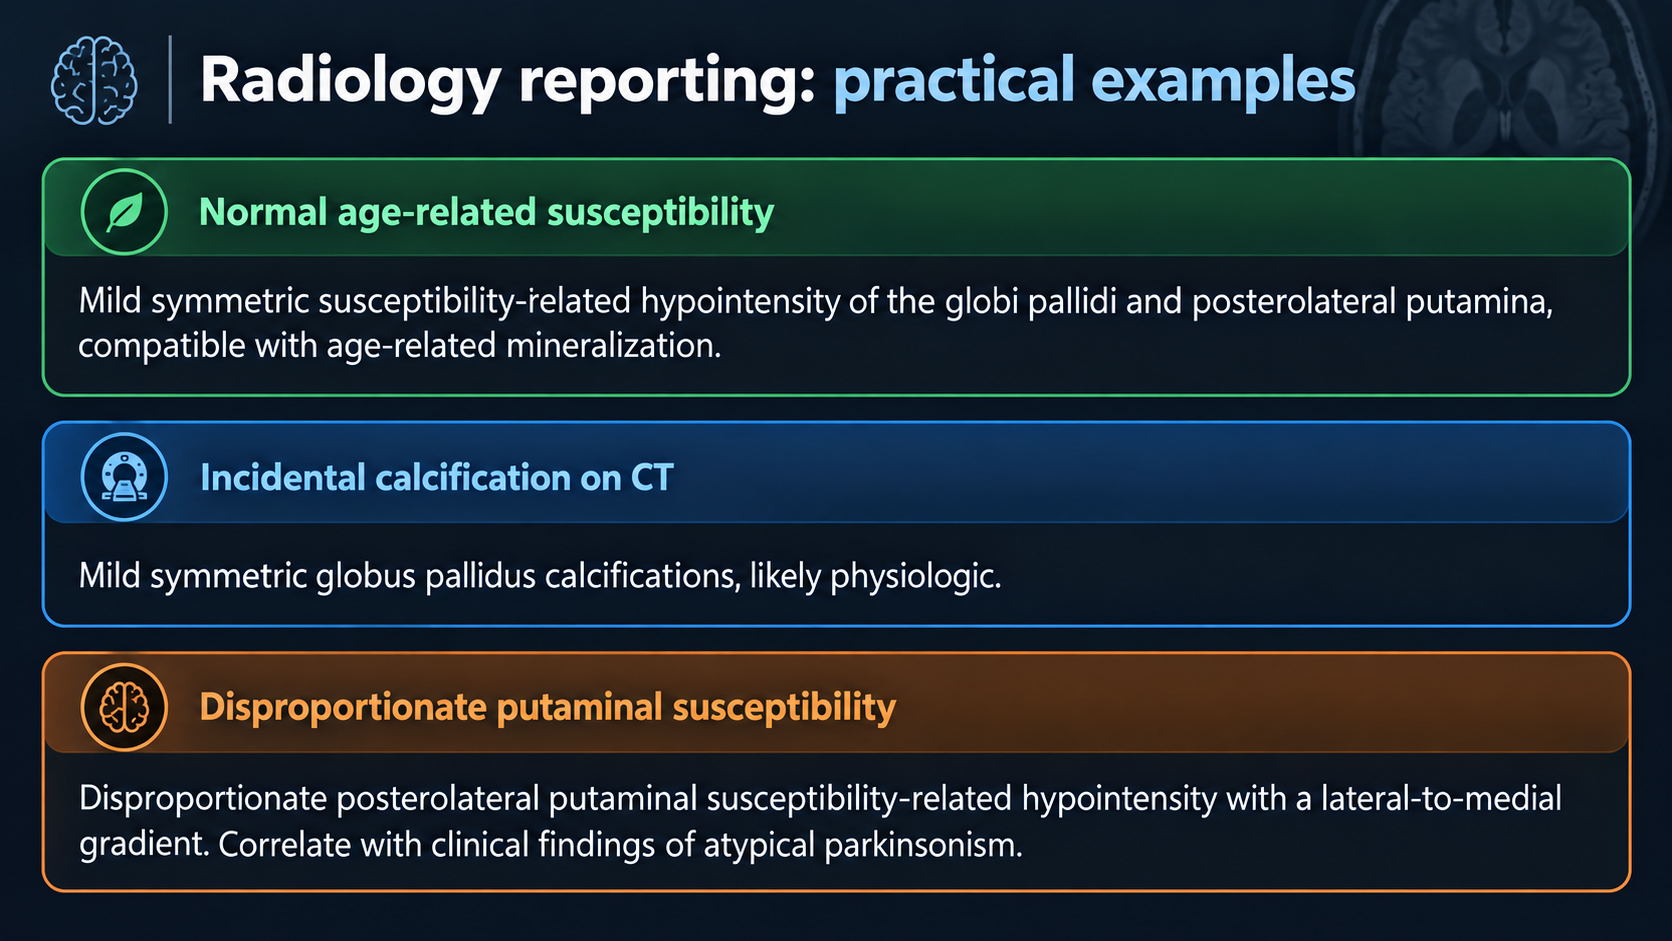
Report physiologic mineralization as 'Mild symmetric susceptibility-related hypointensity of the globi pallidi and posterolateral putamina, compatible with age-related mineralization' or 'Mild symmetric globus pallidus calcifications, likely physiologic' (on CT), emphasizing bilateral symmetry, limited extent, location confined to expected sites, and absence of associated abnormalities—all features that support benign age-related changes.
Pitfalls
- Mistaking a normal posterolateral-to-anteromedial putaminal iron gradient or isolated thin linear lateral putaminal rim for MSA-P; these findings alone are insufficient without putaminal atrophy, abnormal T2 signal, asymmetry, and clinical parkinsonism.
- Overinterpreting symmetric globus pallidus susceptibility changes in older patients as pathologic when they represent expected age-related iron accumulation; correlation with patient age and clinical presentation is essential.
- Relying on susceptibility-weighted imaging alone to distinguish iron from calcium; noncontrast CT is superior for establishing presence and distribution of calcification, and QSM can differentiate based on magnetic susceptibility.
- Failing to recognize that extensive basal ganglia calcification, involvement of multiple deep gray nuclei (putamen, thalamus, dentate nuclei), calcification in cortex or white matter, or findings disproportionate to age warrant metabolic and genetic evaluation beyond simple attribution to normal aging.